Loading…
You’re reading 1 of 342 chapters. Sign in free to unlock the full ED library.Sign in →
IResuscitation and critical careChapter 14
Anaphylaxis
Last reviewed by Dr Sumit Mandal
Anaphylaxis kills by airway oedema, bronchospasm and distributive shock, sometimes all three in the same patient. Intramuscular adrenaline into the anterolateral thigh is the only intervention proven to reduce mortality; everything else is adjunctive.
Bedside bottom line
- Adrenaline 0.5 mg IM into the anterolateral thigh is the only intervention that changes mortality. Give it the moment criteria are met. Do not wait for hypotension.
- Up to 1 in 5 patients have no skin signs. Sudden bronchospasm or hypotension after a likely allergen is anaphylaxis until proven otherwise.
- Steroids and antihistamines treat the rash and the itch, not the airway or the shock. They are adjuncts and have no role in the first five minutes.
Language
Patient leaflets to shareOn this page01 · Recognising anaphylaxis — when to commit
01
Recognising anaphylaxis — when to commit
Any one of three clinical patterns makes anaphylaxis highly likely. Do not wait for hypotension, skin plus airway, or skin plus breathing, is enough.
Bedside key actions
UpdatedWhat's new (2024-2026 update)
- ERC 2025 + RC UK 2025 explicitly advise against routine corticosteroids. Strengthens prior 2021 position
- Refractory anaphylaxis: ECPR is now an option in centres where available (ERC 2025 Special Circumstances)
Diagnostic criteria
- Criterion 1
- Sudden skin/mucosal involvement (urticaria, flushing, lip-tongue swelling) PLUS sudden airway compromise (stridor, hoarseness), respiratory compromise (wheeze, SpO2 < 92%), or hypotension/end-organ dysfunction.
- Criterion 2
- After exposure to a likely allergen, ≥2 of: skin/mucosa, respiratory, cardiovascular (BP drop, syncope), persistent GI symptoms (cramping vomiting).
- Criterion 3
- After exposure to a known allergen for that patient, isolated hypotension qualifies. SBP < 90 mmHg in adults, or > 30% drop from baseline.
Pitfalls
- Watch out
- Up to 20% have NO skin signs: bronchospasm or hypotension after a sting, drug or food in a previously well patient is anaphylaxis until proven otherwise.
- Indian-ED note
- Common triggers: peanut, tree nut, egg, milk, drugs (penicillin, NSAIDs, IV contrast, neuromuscular blockers), Hymenoptera stings, latex. Also consider Type I hypersensitivity reactions to snake antivenom and food-dependent exercise-induced anaphylaxis (wheat).
02
First-line treatment — adrenaline IM
Five things, in this order. Adrenaline IM is the only drug that changes mortality. Antihistamines and steroids are adjuncts. They do not treat the airway or shock.
Bedside key actions
Adrenaline
- Adrenaline dose — adult
- 0.5 mg (0.5 mL of 1:1000) IM into the anterolateral mid-thigh. Use a 21G/23G 25 mm needle; longer in obese patients to clear subcutaneous fat.
- Adrenaline dose — child
- 10 microg/kg IM (0.01 mL/kg of 1:1000), max 0.5 mg. Practical: > 12 yr 0.5 mg · 6–12 yr 0.3 mg · 6 mo–6 yr 0.15 mg · < 6 mo 0.1–0.15 mg.
- Repeat
- Every 5 minutes if no improvement in airway, breathing or circulation. There is no maximum, a third or fourth dose triggers the refractory pathway, not abandonment.
Supportive
- Position
- Supine with legs raised if hypotensive; sitting up only if pure respiratory distress; left lateral if pregnant > 20 weeks. Never stand the patient up, sudden empty-ventricle arrest is reported.
- Fluids
- Crystalloid 20 mL/kg rapid bolus (1 L adult), repeat to total 50 mL/kg in the first 30 min if needed. Loss of intravascular volume into the interstitium can be massive.
- Indian-ED note
- Adrenaline 1:1000 ampoules (1 mg/mL) are universally stocked under EDL. Keep in resus drawer not crash trolley locked box. Cost is negligible; delays are nearly always recognition or training, not supply.
03
What NOT to lead with — common errors
These are the recurring mistakes that turn a survivable anaphylaxis into a death. Each one delays or replaces IM adrenaline.
Bedside key actions
What not to give
- Steroids
- Hydrocortisone and methylprednisolone do nothing in the first 30 minutes. RC UK 2021 (reaffirmed 2025) and ERC 2025 explicitly advise against routine corticosteroids. They neither prevent biphasic reactions nor speed recovery, and steroid use is associated with increased morbidity in observational data.
- Antihistamines
- Chlorphenamine treats urticaria and itch, not airway oedema or shock. Give AFTER adrenaline if at all; oral non-sedating agents (cetirizine 10 mg) are preferred.
What not to do
- IV adrenaline
- Reserve for peri-arrest or refractory shock with cardiac monitoring. Adult bolus 50 microg (0.5 mL of 1:10 000) titrated; or infusion 0.05–1 microg/kg/min. Bolus dosing in the awake patient causes ischaemia, arrhythmia and hypertensive crisis.
Technique
- Route and site
- Anterolateral thigh IM gives peak plasma levels at ~8 min; deltoid is slower and shallower; subcutaneous is unreliable in shock. Auto-injectors deliver into the thigh through clothing.
Pitfalls
- Wait and watch
- Every minute without adrenaline in true anaphylaxis raises the risk of biphasic deterioration and fatal upper airway obstruction. Recognition-to-adrenaline interval is the single biggest modifier of outcome.
04
Refractory anaphylaxis — when 2 IM doses are not enough
Defined as persistent symptoms after 2 appropriate IM doses. Move to an adrenaline infusion and call for senior airway and ICU support early.
Bedside key actions
Drugs
- Adrenaline infusion
- Mix 1 mg in 100 mL 0.9% saline = 10 microg/mL. Start at 0.05–0.1 microg/kg/min and titrate to MAP ≥ 65 mmHg. Run via central or large peripheral line with a clear label.
- Glucagon
- For patients on beta blockers who fail to respond, bypasses the beta receptor. Adult 1–5 mg IV over 5 min then infusion 5–15 microg/min; child 20–30 microg/kg, max 1 mg. Vomiting is common, protect the airway.
Specific issues
- Bronchospasm
- Salbutamol 5 mg + ipratropium 500 microg nebulised in oxygen. IV magnesium 2 g over 20 min for severe wheeze unresponsive to adrenaline.
- Upper airway
- Nebulised adrenaline 5 mg (5 mL of 1:1000) buys time but does not replace early intubation. Call airway-trained senior; have surgical cricothyrotomy kit ready. Laryngeal oedema makes a difficult airway.
Escalation
- Refractory shock
- If MAP < 65 despite adrenaline infusion + 50 mL/kg crystalloid: add noradrenaline 0.05–0.5 microg/kg/min, then vasopressin 0.03 U/min. Methylene blue 1.5–2 mg/kg has anecdotal use in catecholamine-resistant cases.
- Indian-ED note
- Glucagon is not always stocked in district EDs. Alert pharmacy when receiving a beta-blocked patient. Noradrenaline (1 mg/mL) ampoules are universally available; vasopressin often is not below tertiary centres.
05
Observation, biphasic risk and discharge
Every patient gets a minimum observation period stratified by severity. Discharge is conditional on adrenaline auto-injector, written plan, and allergy follow-up.
Bedside key actions
Observation duration
- High-risk = 12 h
- Required > 1 dose of adrenaline, severe asthma background, slow-onset reaction, ongoing trigger exposure, presentation in the evening (limits access to help if biphasic), known biphasic history, or remote home with no immediate access to care.
- Moderate / standard = 6 h
- Resolved with one IM dose, no high-risk features, reliable adult observer at home, lives within easy reach of emergency services.
- Minimum = 2 h
- Mild reaction, single IM dose, isolated cutaneous-respiratory features that resolved within minutes, applies only after senior review.
Discharge
- Auto-injector
- Prescribe 2 devices (adult 0.3 mg, child 15–30 kg 0.15 mg, child > 30 kg 0.3 mg). Demonstrate technique and trainer device before discharge. Competence is the discharge criterion, not just the prescription.
- Tryptase
- Serum mast cell tryptase peaks 1–2 h after onset, falls to baseline by 24 h. Confirms diagnosis retrospectively when in doubt. Send all three samples; comparison to baseline matters more than a single value.
- Indian-ED note
- Adrenaline auto-injectors are not yet on the Indian EDL. Supply is limited and costly (₹6000–8000 each). Where unavailable, train family to draw 0.5 mL from a 1 mg/mL ampoule with a 25 mm 23G needle; document this conversation. Allergy clinics exist in tertiary centres (AIIMS, PGI Chandigarh, CMC Vellore); 108 transfer for any recurrence.
06
After the adrenaline — the discharge that prevents the next one
The resuscitation is the easy half. What decides whether this patient survives the next exposure is a device they can use, a plan they can read, and a trigger they can name.
Bedside key actions
The device
DrugPrescribe two, and make them use the trainer in front of you
Two devices, because a single dose fails often enough that a second is standard, and because one gets lost or expires. Then the part that is routinely skipped: hand over the trainer and watch them do it. Into the outer thigh, through clothing if necessary, held in place, then massage the site. A prescription for a device the patient has never held is a piece of paper, not a treatment. Check the expiry date out loud and tell them to diarise it.
Indian EDIndian-ED note — when there is no autoinjector
Adrenaline autoinjectors are expensive and inconsistently stocked across much of India, so a proportion of your patients will leave without one however good the prescription is. Say so honestly rather than pretending: document that the device was recommended and why it could not be obtained, and build the plan around what does exist, a written card naming the allergen, immediate transport to the nearest facility that stocks adrenaline, and knowing which that is before it is needed. Some families are taught to carry an ampoule and syringe with training; that is a decision for the allergy service, not a default from the ED.
The plan
ApproachThe written action plan is the intervention, not the leaflet
One page, in the language the family actually reads: the named allergen, what the early symptoms look like, the instruction to use adrenaline FIRST rather than waiting to see, the position to lie in. Flat with legs raised, and never suddenly upright, because posture change has been associated with deterioration. Call for help, and a second dose after five minutes if there is no improvement. Give a copy to the patient and, for a child, to the school.
- Name the trigger, or say plainly that you could not
- Work through what was eaten, taken, injected or stung in the four hours before onset, and note the less obvious ones: a new medication started that week, non-steroidal anti-inflammatories, an exercise-associated reaction where food alone is tolerated but food plus exertion is not, and delayed reactions hours after red meat. Where no trigger is found, write idiopathic rather than leaving the box empty. It changes the referral urgency and it stops the next clinician assuming the work was done.
07
The allergy label — and why removing a wrong one is a clinical act
Most people labelled penicillin-allergic are not. The label follows them for life, pushes them onto worse antibiotics, and is associated with worse outcomes, and there is a validated bedside rule for sorting it.
Bedside key actions
Sorting it
ApproachAsk what actually happened — most labels are not allergy
A large majority of reported penicillin allergy does not survive formal testing. The common histories are childhood rashes during a viral illness that was being treated with an antibiotic, gastrointestinal upset, headache, or a family member's allergy transferred onto the patient. Ask three things: what happened, how long after the dose, and how long ago. Nausea and diarrhoea are intolerance, not allergy, and they belong in a different box on the chart.
PearlThe validated rule, and what a low score means
A four-item clinical decision rule scores the reaction on whether it occurred within the last five years, whether it was anaphylaxis or angioedema, whether it was a severe cutaneous adverse reaction, and whether it required treatment. A very low score identifies patients at minimal risk in whom the label is very unlikely to be real. What that permits is a confident REFERRAL for de-labelling, not a challenge dose in the emergency department, which is not the place for it.
Why it matters
DrugThe cross-reactivity figure you were taught is wrong
The traditional teaching of roughly ten percent cross-reactivity between penicillins and cephalosporins is far too high. Cross-reactivity tracks the similarity of the R1 side chain rather than the shared beta-lactam ring, so cephalosporins with dissimilar side chains carry very low risk. Practically: a remote, mild penicillin rash should not by itself deny a patient a cephalosporin when that is the right drug. But a documented anaphylaxis to any beta-lactam is a different conversation and needs specialist input.
PearlWhy this belongs in an emergency chapter at all
Because the ED is where the label is most often acted on and least often examined. A wrong penicillin label pushes patients onto broader, more toxic and less effective alternatives, with more Clostridioides difficile and more resistant organisms, and it is associated with worse outcomes in serious infection. Two minutes of history in a patient who is not acutely allergic today, written clearly into the record, is a genuine intervention, and writing 'penicillin allergy: rash aged 6, no angioedema, tolerated cephalexin since' is worth more than the word allergy alone.
Key takeaways
- Adrenaline 0.5 mg IM into the anterolateral thigh is the only intervention that changes mortality. Give it the moment criteria are met. Do not wait for hypotension.
- Up to 1 in 5 patients have no skin signs. Sudden bronchospasm or hypotension after a likely allergen is anaphylaxis until proven otherwise.
- Steroids and antihistamines treat the rash and the itch, not the airway or the shock. They are adjuncts and have no role in the first five minutes.
- Refractory anaphylaxis (still unwell after 2 IM doses) needs an adrenaline infusion, not more boluses, and glucagon if the patient is on a beta blocker.
- Discharge requires two auto-injectors, a written action plan, demonstrated technique, and an allergy clinic referral. Without these, the next reaction is the fatal one.
- Prescribe TWO adrenaline autoinjectors and make the patient use the trainer in front of you, a prescription for a device they have never held is paper, not treatment.
- Autoinjectors are expensive and patchily stocked in India. Where one cannot be obtained, document that plainly and build the plan around the nearest facility that stocks adrenaline.
- The written action plan must say use adrenaline FIRST rather than wait and see, lie flat with legs raised, and never sit or stand the patient up suddenly.
- If no trigger is identified, write 'idiopathic' rather than leaving it blank. It changes referral urgency and stops the next clinician assuming the work was done.
- Most reported penicillin allergy is not allergy. Ask what happened, how soon after the dose, and how long ago. Nausea and diarrhoea are intolerance and belong in a different box.
- A validated four-item rule: reaction within 5 years, anaphylaxis or angioedema, severe cutaneous reaction, treatment required, identifies very-low-risk labels. A low score earns a REFERRAL for de-labelling, not a challenge dose in the ED.
- The taught 10% penicillin-cephalosporin cross-reactivity figure is far too high: risk tracks R1 side-chain similarity, not the beta-lactam ring.
- Write the allergy history, not the word: 'rash aged 6, no angioedema, tolerated cephalexin since' is worth more to the next clinician than 'penicillin allergy'.
Test yourself
CME · 20 vignettesClinical vignettes built from this chapter. Pass ≥70% to earn a printable 0.5 CME certificate.
Sign in to take the quiz and earn a certificate.
Patient leaflets to share
Print it, or send it on WhatsApp — the “While in the ED” sheets during the stay, the rest before the patient leaves. Choose Hindi, Hinglish or English on the next screen.
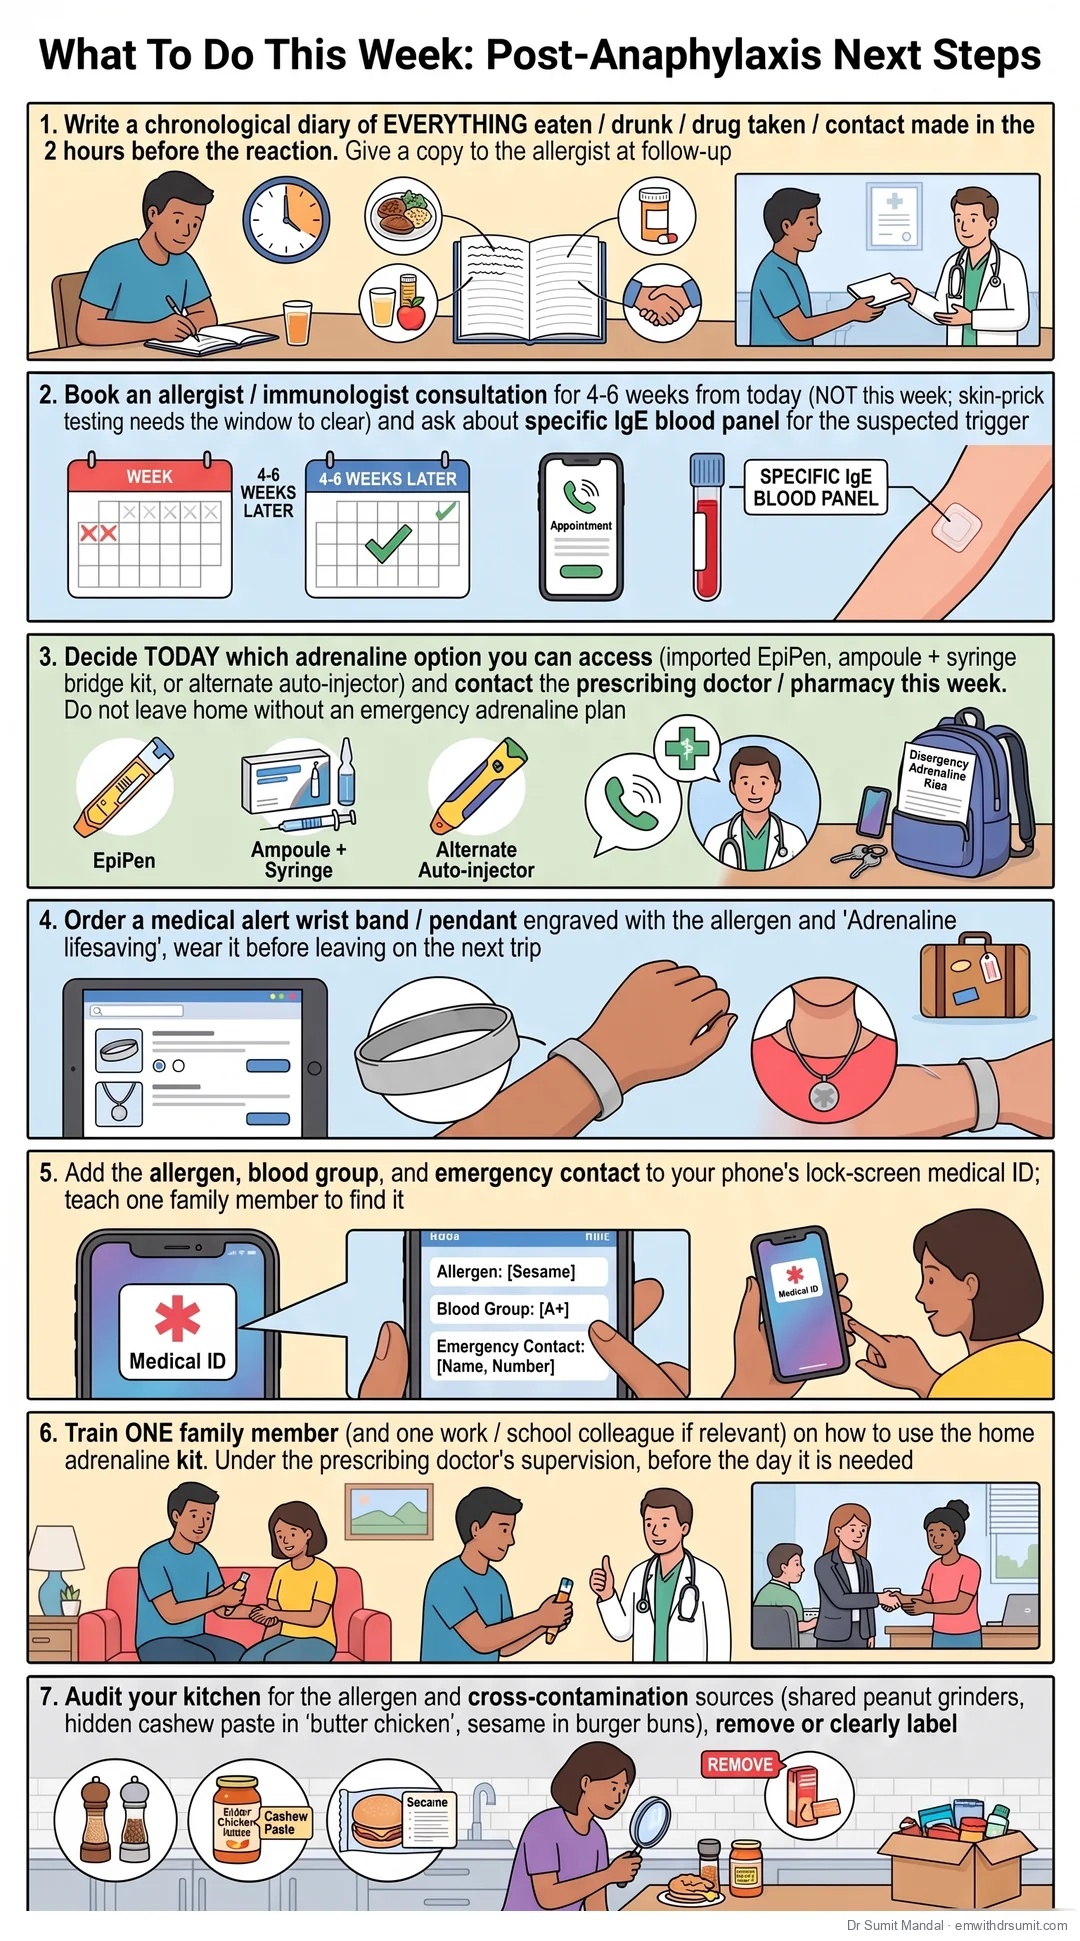 Discharge leaflet · 3 picturesGoing home after anaphylaxis — the next 72 hours, the next allergen-free year, the EpiPen reality in IndiaPrint / share →
 Discharge leaflet · 3 picturesGoing home with hives (urticaria) — take the antihistamine every day until it settles, and know the swelling and breathing signs of a severe reactionPrint / share →
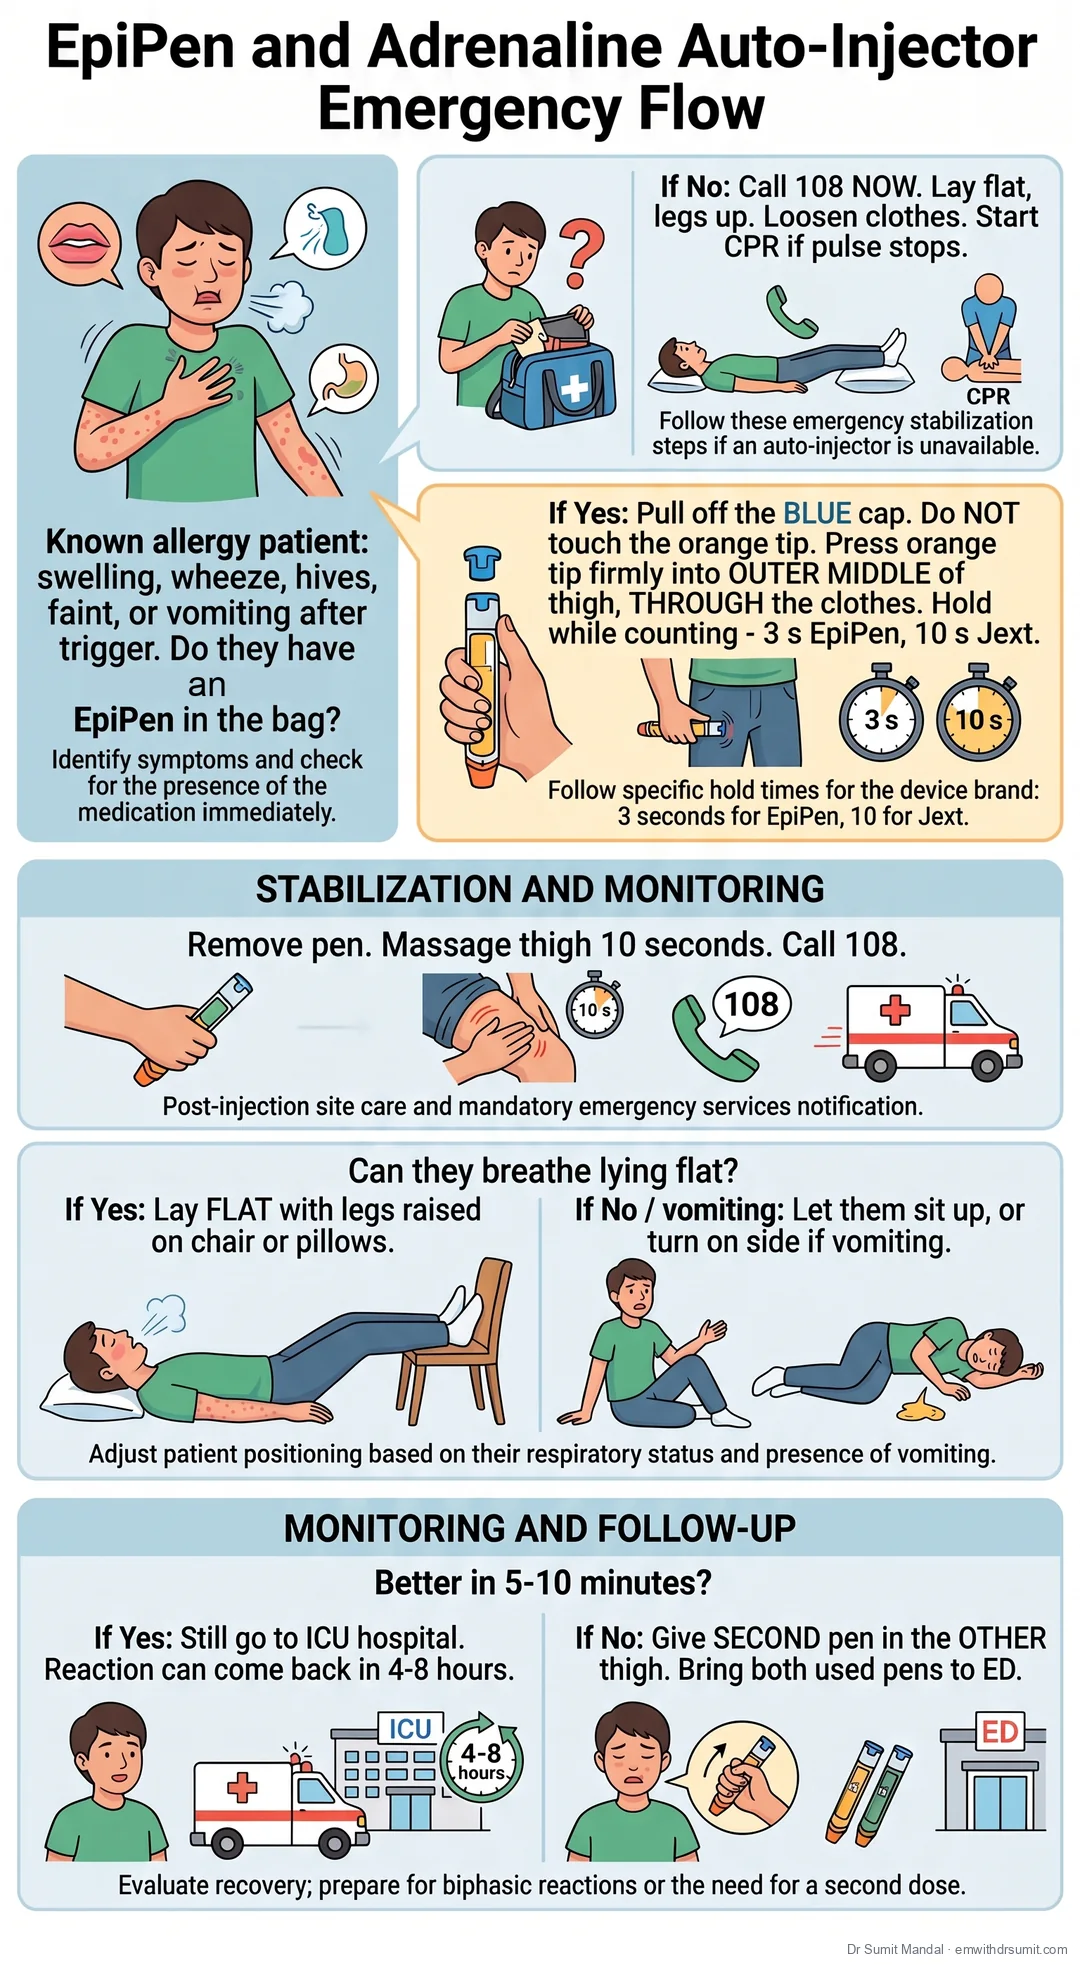 First aid at home · 3 picturesEpiPen / adrenaline auto-injector — through clothes, outer thigh, hold while you countPrint / share →
References
Freely citableEvery clinical claim in this chapter is backed by an independent, freely-accessible guideline. Tap any reference to open the source on the issuing body's site.
- RC UK 2025 AnaphylaxisUK
Resuscitation Council UK 2025 — Emergency treatment of anaphylaxis: guidelines for healthcare providers
“Adrenaline should be given as soon as the diagnosis of anaphylaxis is suspected. The intramuscular route is recommended for most healthcare providers.”
Open source ↗
- NICE CG134 (2020 update)UK
Anaphylaxis: assessment and referral after emergency treatment
Open source ↗
- WAO 2020 — anaphylaxisGlobal
World Allergy Organization Anaphylaxis Guidance 2020
Open source ↗
- ERC 2025Europe
European Resuscitation Council Guidelines 2025 — Cardiac Arrest in Special Circumstances (anaphylaxis)
Open source ↗
- Indian Academy of Allergy & Asthma — Anaphylaxis (2023)India
IAAA position statement on anaphylaxis recognition and adrenaline use
Open source ↗
- EAACI anaphylaxis (2021 update)Europe
EAACI guidelines: anaphylaxis — 2021 update
Open source ↗
- PEN-FAST (JAMA Intern Med 2020)Global
Development and validation of a penicillin allergy clinical decision rule
Open source ↗
- Cephalosporin side-chain cross-reactivityUS
Cephalosporin side-chain cross-reactivity — the R-group basis for beta-lactam allergy risk
Open source ↗
- Resuscitation Council UKUK
Emergency treatment of anaphylaxis — Resuscitation Council UK guidance
Open source ↗
Compiled from contemporary emergency-medicine practice and the guidelines listed above. For registered medical practitioners; not a substitute for clinical judgement.
Study with Dr Sumit
Like this chapter? There are 341 more.
Visual ED study chapters across resuscitation, trauma, cardiovascular, respiratory, neurology, toxicology, paediatrics and more, all built for working clinicians in Indian EDs and beyond. Plus calculators, decision rules, and clinical algorithms.
No clinical decisions should rest on a single source. Always cross-check with local protocols. Educational use only.